
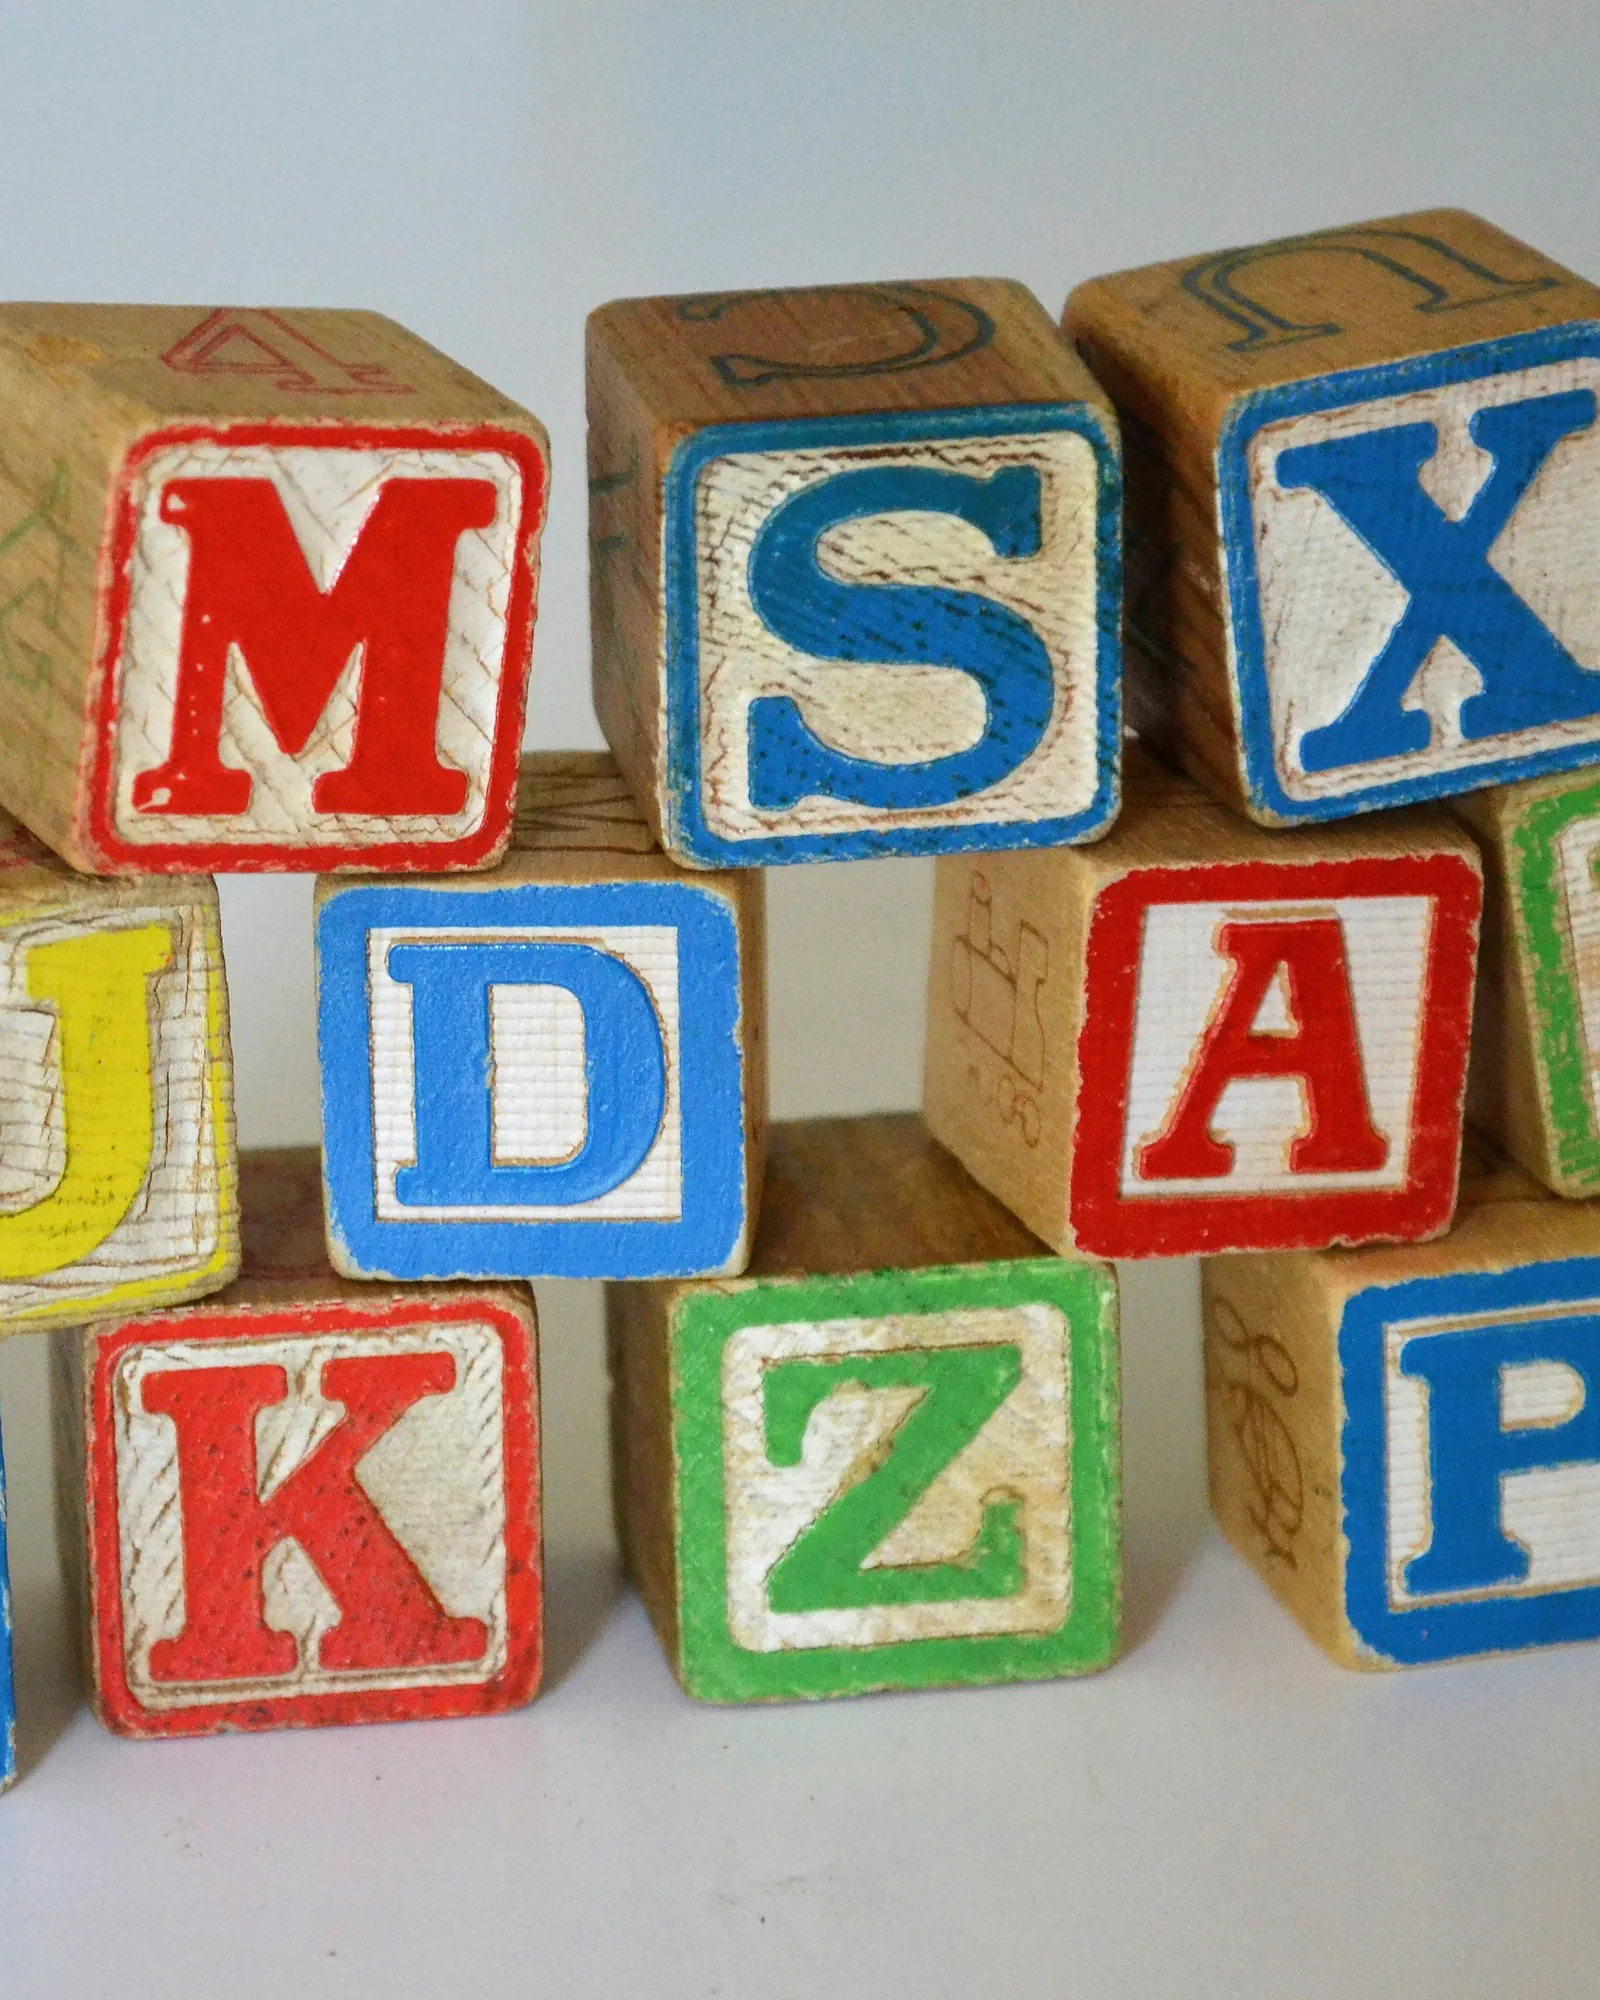
Ask most people what dyslexia looks like and you will hear the same answer: letters that flip around on the page. It is a tidy image, easy to remember, and it has shaped how families and even some educators decide whether reading difficulty is worth investigating. The trouble is that it describes a narrow slice of the picture at best. Plenty of children who reverse their b's and d's are simply young, and plenty of children with genuine dyslexia never reverse a letter in their lives.
That gap between the myth and the reality has real consequences. Bright, verbally capable kids get told they are not trying hard enough. Adults who compensated their way through school assume they were just bad at English. Families wait for the obvious sign that never comes. This post clears up what dyslexia actually involves, describes the patterns clinicians tend to see, and explains what a comprehensive evaluation looks for. Reading profiles vary widely from person to person, so nothing here is a substitute for an assessment with a qualified clinician. It is meant to help you ask better questions.
Where the Reversed-Letters Idea Came From
Early theories about reading difficulty focused on vision, and the phrase "word blindness" circulated for decades. Visual reversals were the most noticeable surface feature, so they became the shorthand. That framing lingered in popular culture long after the research moved on, which is why so many people still picture a page of jumbled type when they hear the word dyslexia.
Contemporary understanding places dyslexia in the language system rather than the visual system. The core difficulty involves connecting the sounds of spoken language to the letters that represent them. Letter reversals can occur, but they are a byproduct rather than the mechanism, and they are developmentally typical in early elementary school. Relying on reversals as the entry ticket to an evaluation means missing the children whose difficulty lives somewhere less visible.
What Dyslexia Actually Involves
Dyslexia is best understood as a specific learning disorder affecting accurate and fluent word recognition, along with spelling and decoding. It is neurobiological in origin, it tends to run in families, and it occurs across the full range of intelligence. That last point matters enormously, because the most common reason a family delays seeking help is that the child seems too bright to have a reading problem.
The mismatch is actually the signature. A child who discusses a documentary in sophisticated detail but stumbles through a paragraph aloud is showing you exactly the profile that warrants a closer look. Clinicians routinely see this pattern in students whose oral vocabulary and reasoning are strong while their word-level reading lags well behind. Our overview of the learning differences we assess describes how reading, writing, and math difficulties are considered together rather than in isolation.
The Signs That Are Easier to Miss
Because the core difficulty is phonological, the observable signs are often behavioral or indirect. The following patterns come up frequently in clinical interviews, and none of them involves a flipped letter.
Effortful, Word-by-Word Reading
The most reliable marker is not accuracy alone but fluency. A student may eventually get the words right while sounding labored, losing the rhythm of the sentence, or finger-tracking well past the age when that usually fades. Because comprehension depends on reading smoothly enough to hold meaning in mind, slow decoding quietly degrades understanding. Families often notice this most during homework, when a passage that should take five minutes stretches into thirty.
Spelling That Does Not Improve With Practice
Spelling frequently lags further behind than reading and responds poorly to repetition. Words spelled correctly on Friday's test are gone by Monday, and written spelling may be phonetically inventive in ways that reveal how the sounds are being mapped. Handwritten work can also look shorter and simpler than the child's spoken ideas, because avoiding hard-to-spell words limits vocabulary on the page.
Trouble Retrieving Words on Demand
Many students with dyslexia describe knowing exactly what they mean while the specific word refuses to arrive, and rapid naming of familiar items, letters, or numbers can be notably slow. Because this looks like hesitancy or distraction, it is often chalked up to shyness rather than recognized as part of a language-based profile. We explore the broader version of this in our article on word-finding difficulties and what testing can clarify.
Avoidance, Fatigue, and Stomachaches
When reading is exhausting, children develop reasonable strategies to reduce exposure to it. That can look like clowning around during silent reading, lengthy trips to the bathroom, refusing to read aloud, or genuine physical complaints on school mornings. It is worth saying plainly that these behaviors are usually protective rather than defiant, and understanding the reading difficulty underneath often changes the whole conversation at home.
What a Comprehensive Evaluation Looks For
A real dyslexia evaluation goes well beyond a reading level. The point is to identify which component of the reading process is breaking down, rule out other explanations, and generate recommendations specific enough to act on.
1. Underlying Cognitive and Language Abilities
Testing begins with a broad look at reasoning, verbal comprehension, working memory, and processing speed. This establishes context and helps distinguish a specific reading difficulty from a more global learning profile, which calls for different supports. It also protects against the assumption that a struggling reader must have limited ability, and documenting genuine strengths is often the most validating part of the process for a discouraged student.
2. Phonological Processing and Rapid Naming
These are the closest things to core markers. Clinicians assess awareness of sound structure in spoken words, the ability to hold and manipulate sounds, and how quickly familiar symbols can be named. Because these skills can be tested before a child reads much at all, they are especially useful for early identification in kindergarten and first grade.
3. Word Reading, Decoding, and Fluency
Real and nonsense words are both assessed, because nonsense words reveal decoding skill without letting memorized sight vocabulary mask the difficulty. Timed oral reading of connected text captures fluency, which is frequently the most impaired area in bright compensating readers. Comprehension is measured both when the student reads and when a passage is read aloud to them, and a large gap between those two conditions is highly informative.
4. Written Expression, Spelling, and Math Screening
Spelling and writing samples show how the phonological difficulty appears in output, and a math screening checks whether a second learning difference is present. Co-occurring conditions are common, and attention difficulties in particular can complicate the picture, so ruling these overlaps in or out prevents a partial answer that leads to a partial support plan.
5. History, Records, and Educational Context
Testing scores mean little without history. Clinicians review report cards, prior interventions, teacher observations, family history, and the child's own description of school. If a student has already received solid reading instruction and still struggles, that is meaningful evidence rather than a reason to wait longer.
Taken together, these components produce a specific profile rather than a label, and that specificity is what makes the resulting recommendations useful. Our page on what a learning disorder evaluation involves for children and teens walks through the sessions in order.
What Families Do With the Results
An evaluation is only as valuable as what follows it, which is why the written report matters so much. A strong report translates test data into decisions the people around the student can actually make. If you are curious what that document contains, we break it down in our guide to what a psychological evaluation report includes.
In practice, results typically inform several concrete things:
- Eligibility conversations with the school and the specific category under discussion
- The type of reading instruction recommended, particularly structured, explicit approaches to phonics and decoding
- Classroom and testing accommodations such as extended time, audio texts, or reduced copying demands
- Assistive technology like text-to-speech and speech-to-text tools
- Language for the student to use about their own learning, which tends to reduce shame considerably
Results also matter for adults. Many people reach college, graduate programs, or professional licensing exams before anyone formally documents a reading difficulty they have managed around for years, and timely documentation is often required for accommodation requests.
Getting a Clearer Answer
Dyslexia is common, well characterized, and highly responsive to the right instruction, which is precisely why a vague explanation is such an expensive thing to accept. If a capable student is struggling to read, the question is not whether they are trying. The question is which part of the reading process needs direct support, and that is answerable. Every profile is different, and the appropriate plan depends on the individual, so this kind of question is best worked through with a qualified clinician who can see the whole picture.
If you have been wondering whether reading difficulty in your household deserves a closer look, we would welcome the conversation. You can read about how our evaluation process unfolds from intake to feedback and then reach out with your questions. Clear answers tend to make the next school year look very different.

Dr. Brooke Colman, PsyD, LP
Dr. Brooke Colman is a licensed clinical psychologist and the owner of Encore Psychology in Bloomfield Hills, Michigan. She specializes in evaluations for ADHD, autism, and learning differences for clients ages 2 and up, as well as accommodations evaluations for high-stakes exams. Through PsyPACT, she offers telehealth to clients in 40 states.
